
Neurology Practice Management
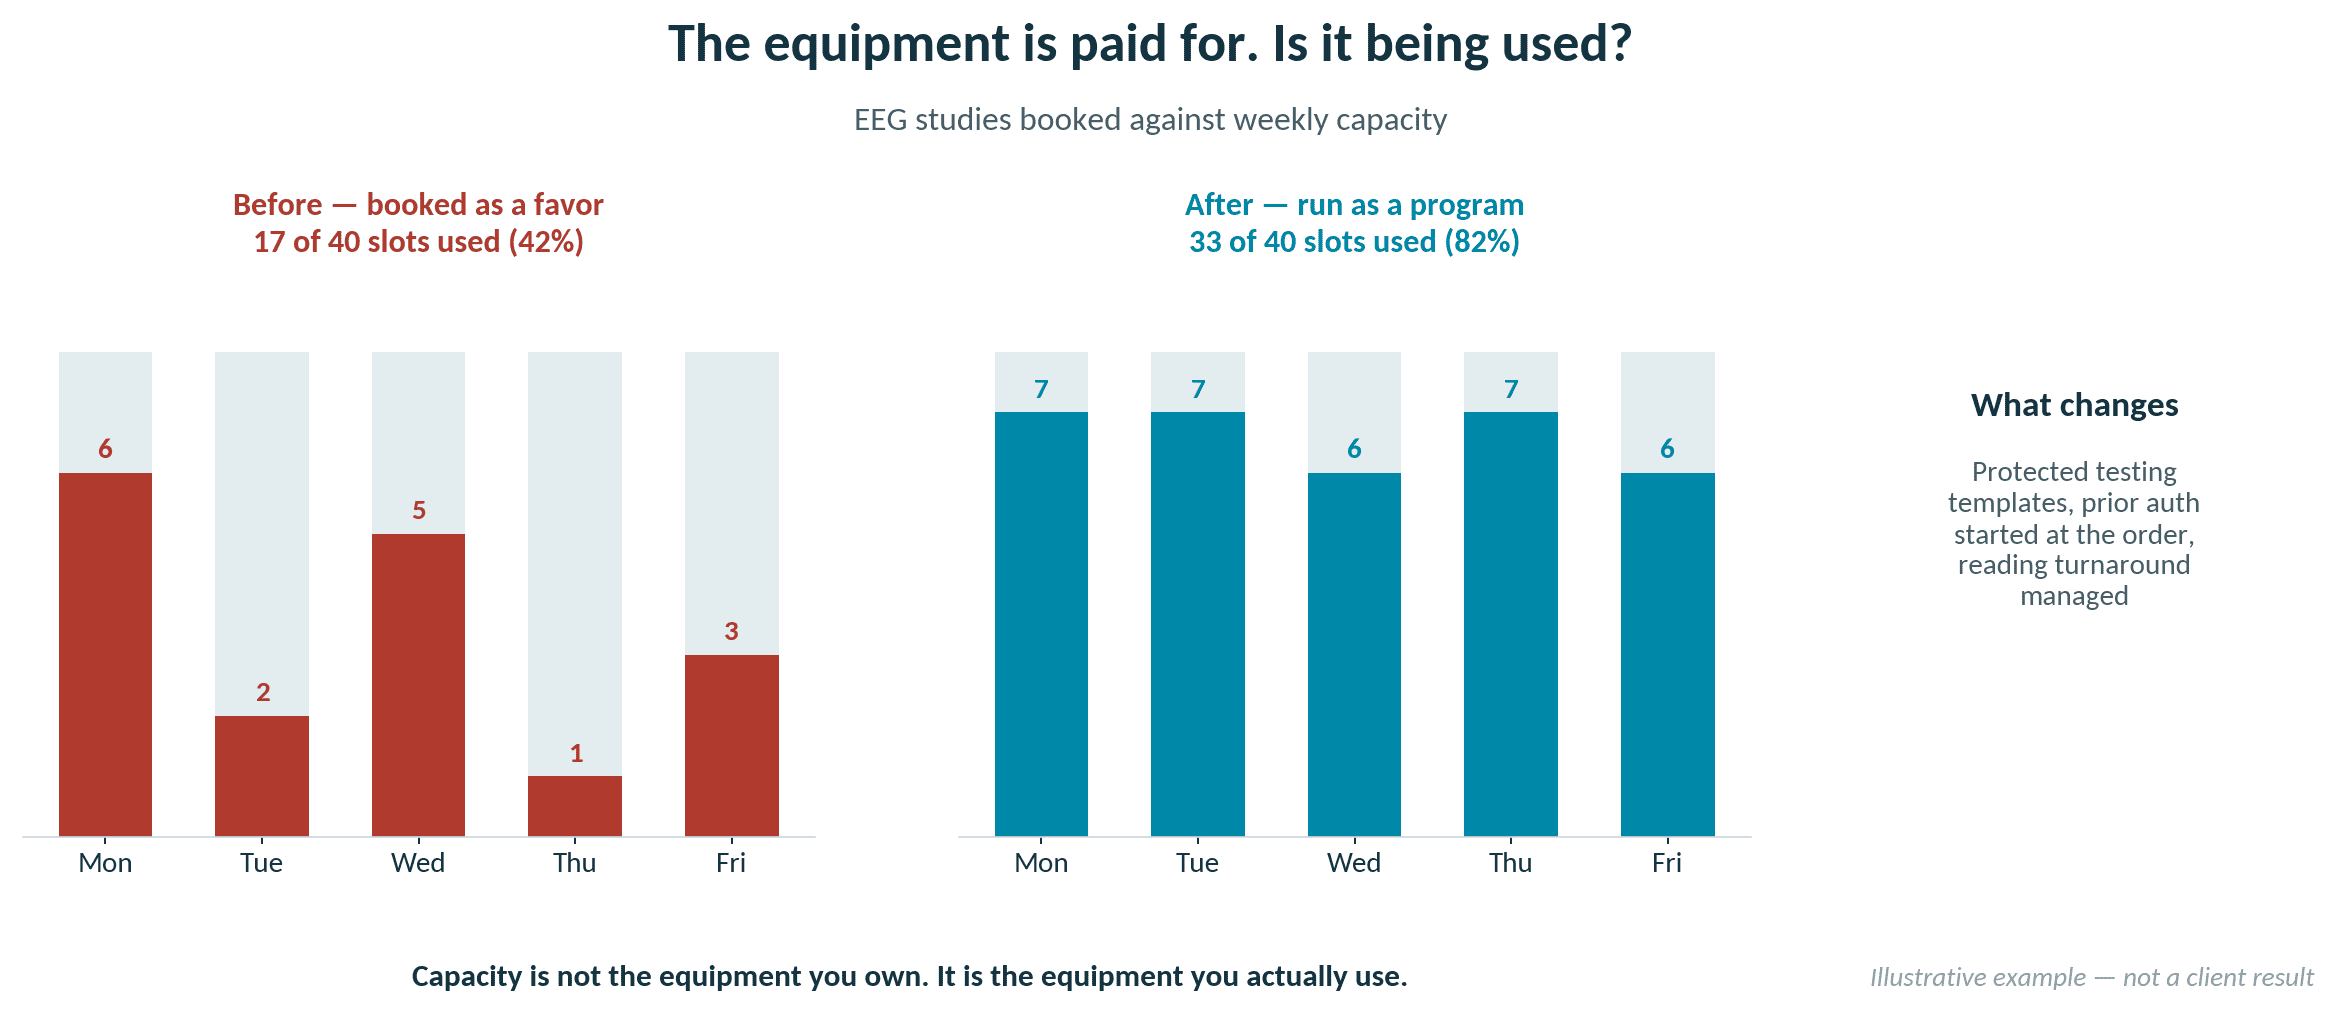
Most neurology practices we meet already own the capability to earn considerably more than they do. The EEG equipment is there. The biopsy service is offered. The clinical demand is real.
What is missing is the operating layer — scheduling templates that keep testing days full, documentation that survives a payer review, and denial work done at the point of origin rather than ninety days later.
We build the operating layer, and then we run it.
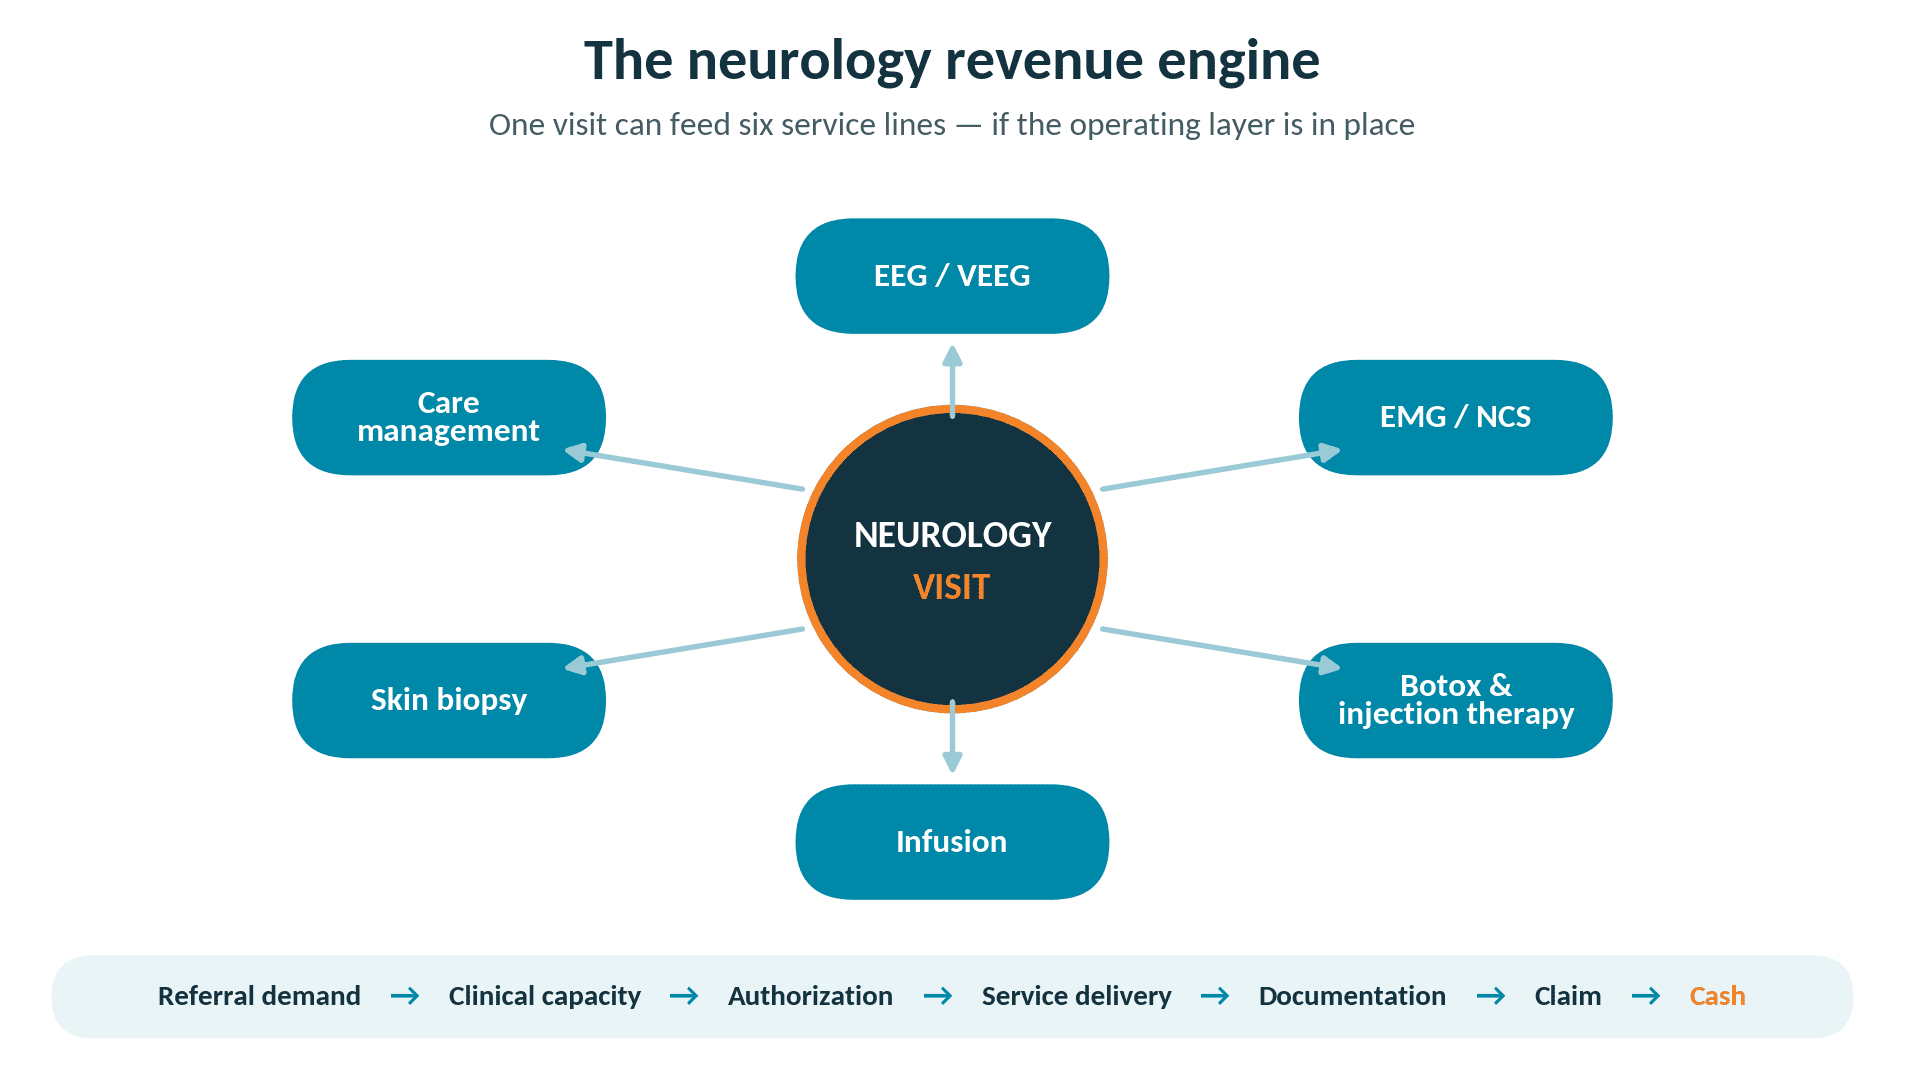
Service lines we build and operate
Each is a program with its own scheduling, authorization, documentation, coding and follow-up requirements. We treat them that way.
| DIAGNOSTICS | PROCEDURES & THERAPEUTICS | LONGITUDINAL CARE |
|---|---|---|
| EEG Technical and professional components billed correctly; reading turnaround managed |
Botox & Injection Therapy Buy-and-bill economics, prior auth and drug waste documentation |
Transitional Care Management Post-discharge follow-up built into the schedule |
| Ambulatory VEEG Patient selection, equipment logistics and the prior auth pathway |
Infusion Authorization, scheduling and drug billing workflow |
Remote Therapeutic Monitoring Enrollment, time tracking and monthly billing |
| EMG / NCS Scheduled against provider availability; documentation that supports units |
Skin Biopsy Programs Workflow, specimen handling, lab coordination, documentation and billing requirements by clinical indication |
Care Management Recurring revenue that does not depend on clinic capacity |
| VNG Testing blocks and documentation built for volume |
We also support cognitive testing and imaging pathways where the practice has the volume.
Where neurology revenue gets stuck
- Testing capacity not fully scheduled - Equipment exists, but templates do not maximize utilization.
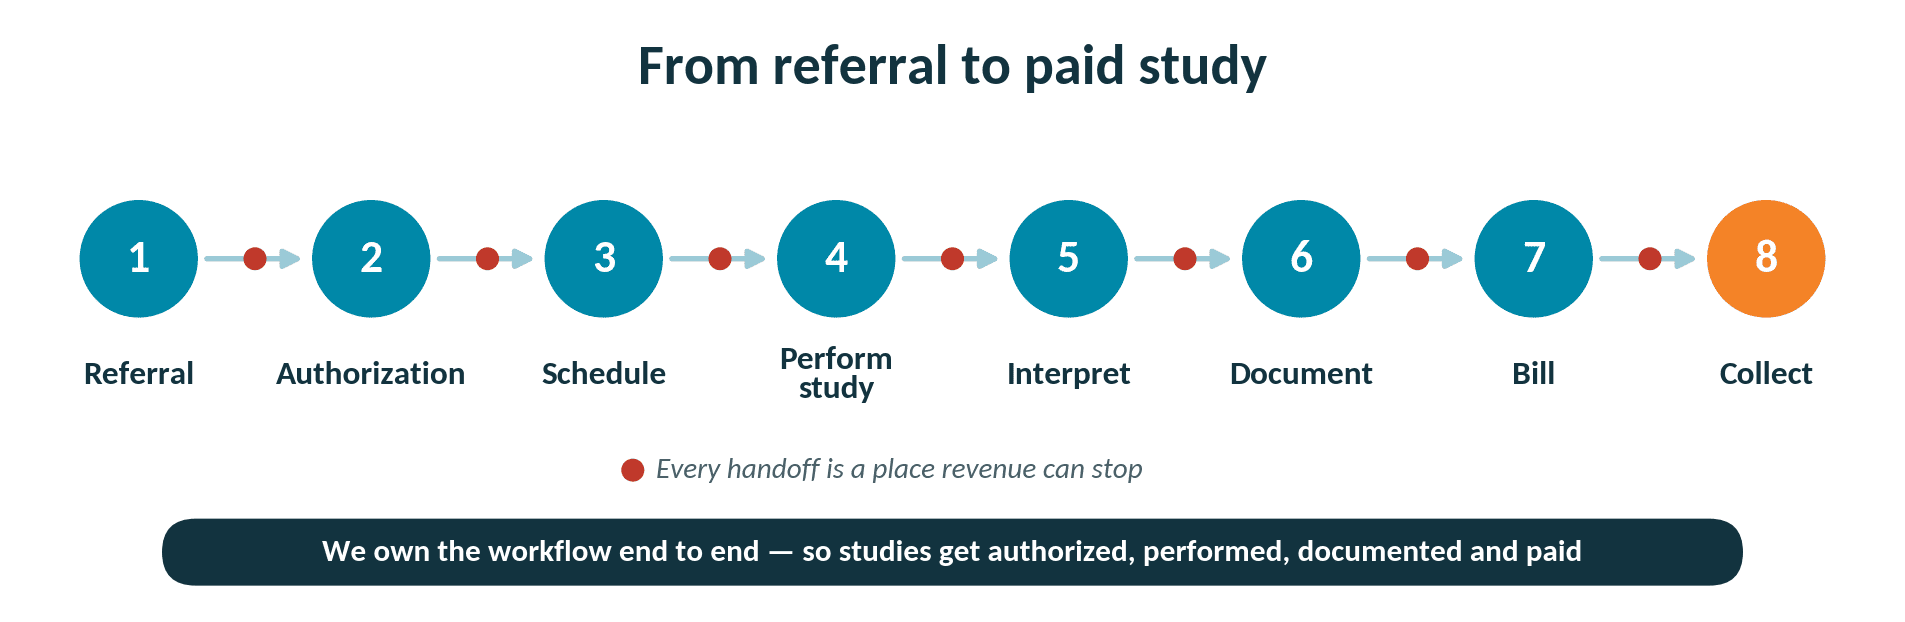
- Authorizations delay procedures - Studies wait because ownership and follow-up are unclear.
- Services performed but not captured - Documentation, units or charge workflows break down.
- Referrals never reach the right service line - Demand exists, but the workflow fails to convert it.
- Denials worked after the fact - Instead of prevented at the source.
How we operate in neurology
| GROWTH Referral growth, new locations, specialty service-line expansion |
REVENUE Ancillary programs, payer strategy, charge capture |
PROFIT Denials, A/R, documentation, utilization |
OPERATIONS Scheduling, authorization, eCW optimization, KPI ownership |
What typically moves
| ↑ 20–40% Collections |
↓ 15–25% Days in A/R |
↑ 10–20% Provider productivity |
1–3 New revenue streams |
Ranges reflect outcomes observed across engagements and are not a guarantee of results.
We quantify the revenue, operational and growth opportunities already inside the practice — before recommending what to build next.