
Primary Care Practice Growth & Operations
Independent primary care and internal medicine practices deliver far more value than a traditional office visit captures. The opportunity is not simply more appointments — it is capturing the value of care already being delivered across the patient journey, with a schedule that can absorb the demand.
We model the economics, build the workflow and stay through execution.
Where we create value
Revenue Performance
Coding, charge capture, denials, A/R, payer performance and collections — including the longitudinal-care add-on on every qualifying visit.
Provider Productivity
Physician and APP schedules, staffing, workflows and patient access — so the panel can grow without longer days.
Longitudinal Care
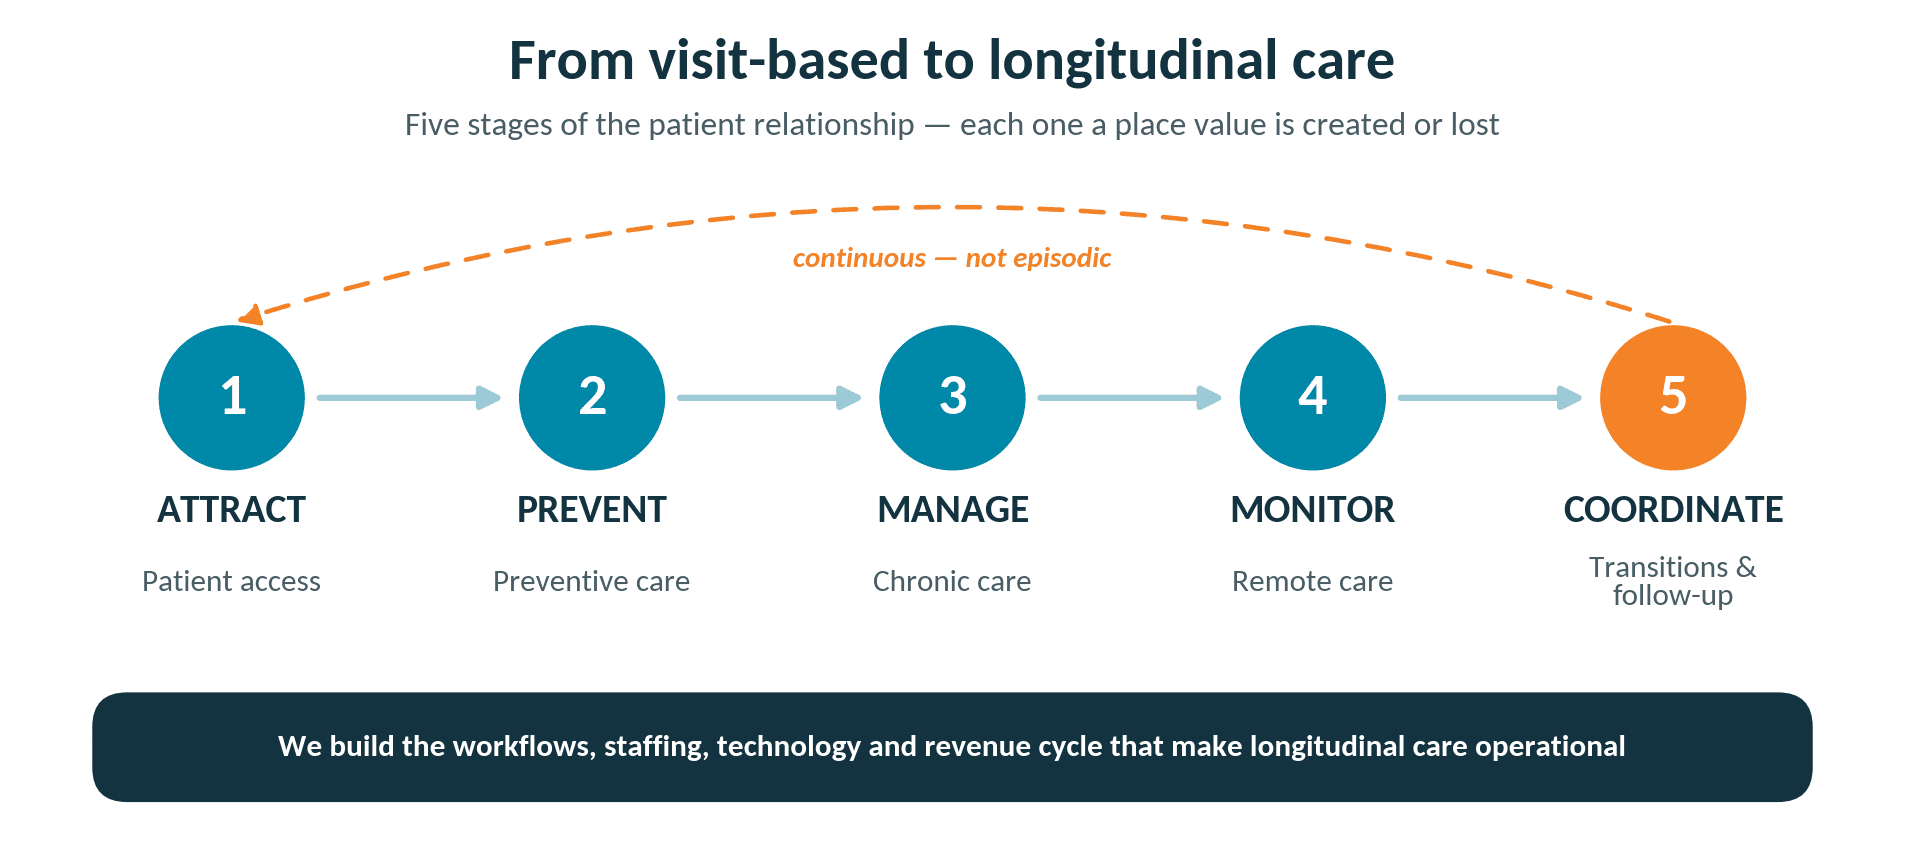
Repeatable preventive, chronic-care, transitional and remote-care workflows.
Growth & Payment Strategy
New services, providers, locations and value-based payment opportunities, evaluated on their real economics.
Build the primary revenue platform
| Preventive & transitional care | Annual wellness visits · Transitional care management · Advance care planning · Preventive counseling Work many practices already perform but do not capture consistently — including counseling such as obesity and tobacco cessation — built as programs with the required elements documented. |
| Longitudinal care management | Advanced primary care management · CCM · PCM The right model for each patient, including Medicare's monthly primary care management bundle — built as a care-management operation, not another code. |
| Remote care | Remote physiologic monitoring · Continuous glucose monitoring programs For hypertension, diabetes and other chronic conditions, with coverage and payer requirements validated before launch. |
| Integrated behavioral health | Behavioral health integration · Collaborative care Behavioral health managed inside the practice, including pathways that pair with advanced primary care management. |
| Value-based revenue | ACO participation · Shared savings · Quality incentives · Prospective payments Arrangements that can make revenue larger and more predictable — including models designed for independent practices — evaluated before you sign. |
Don't add programs just because they can be billed
Before we recommend a new program, we test it against the practice:
| Patient panel → Eligibility → Payer mix → Reimbursement → Staffing → Workflow → Technology → Compliance → Break-even |
| BUILD The clinical and financial case works |
WAIT Good opportunity, wrong timing |
PASS The economics or operating model do not support it |
We determine what fits the practice before recommending what to build.
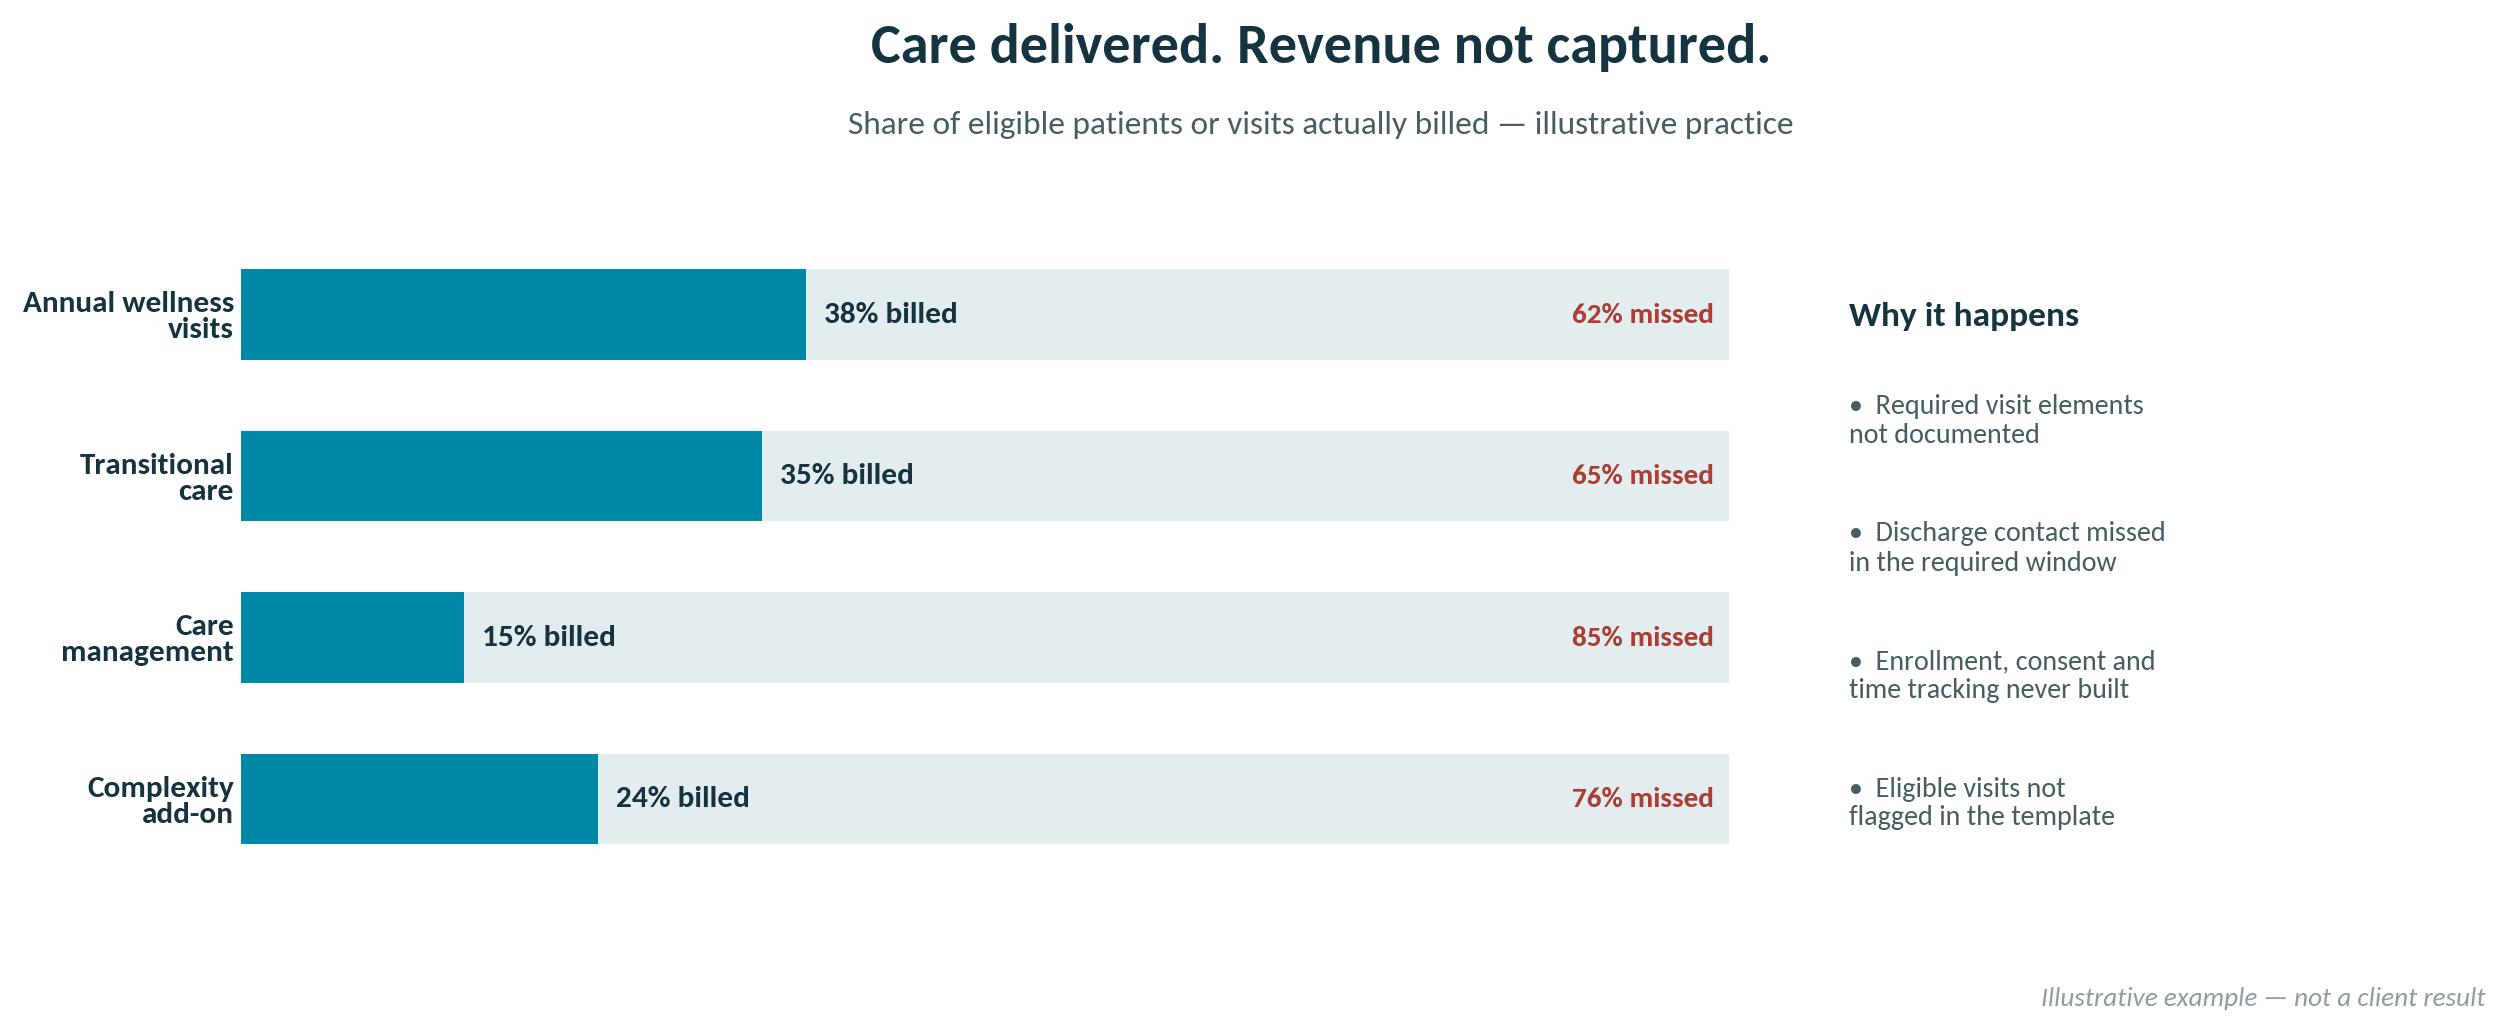
Program eligibility, consent, documentation and billing rules are built in before launch. Care management and remote monitoring are active audit areas, and we treat them that way.
What we measure
Depending on the baseline and engagement, targets may include:
| ↑ Collections Capture revenue already being earned. |
↓ Days in A/R Improve cash conversion. |
↑ Provider capacity More productive clinical time without simply adding hours. |
↑ Preventive & care-management capture Identify eligible patients and close workflow gaps. |
↑ Patient access & retention Stronger scheduling, follow-up and continuity. |
Targets are set after a baseline assessment and vary by practice, payer mix and scope of engagement.
A stronger primary care practice — beyond the office visit.
Independent primary care can build stronger economics without giving up the physician-patient relationship that makes it valuable. We find where revenue is being missed, decide which opportunities make sense, and build the operation to execute them.
A Discovery & Opportunity Assessment identifies revenue gaps and models which service lines may fit your patient volume, payer mix and operating capacity.